



Evaluating the Role of Mitochondrial Dysfunction in Muscle Cell Differentiation in an iPSC-derived Skeletal Muscle Model of Barth Syndrome
Annual Clinical Genetics Meeting, March 2026
Valeria A. Silva, Johns Hopkins University School of Medicine, Valeria A. Silva, Olivia Sniezek-Carney, PhD, Kyuna Lee, BS, Kathryn C. Chatfield, MD PhD, Genevieve Sparagna, PhD, Anne Hamacher-Brady, PhD, Hilary J. Vernon, MD, PhD, FACMG
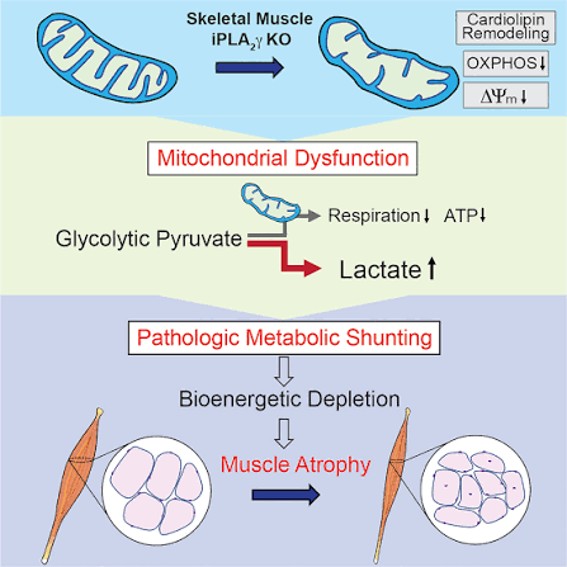
Introduction: Barth syndrome (BTHS) is a rare, X-linked mitochondrial disease caused by pathogenic variants in TAFAZZIN (TAZ). Tafazzin is an acyltransferase that catalyzes the final step in remodeling of mature cardiolipin (CL), a lipid in the inner mitochondrial membrane that is essential for respiratory chain assembly, mitophagy, and mitochondrial structure. Mutations in TAFAZZIN result in abnormal CL remodeling, including accumulation of monolysocardiolipin (MLCL) and reduction of mature CL, which clinically manifests as cardiomyopathy, low skeletal muscle mass, skeletal myopathy, and neutropenia. The skeletal muscle in BTHS is characterized by postnatal muscle dysfunction with exercise intolerance, fatigue, and progressive myopathy. These skeletal muscle (SKM) symptoms significantly impair quality of life, highlighting the importance of understanding the role of TAFAZZIN deficiency in developing muscle. We hypothesize that abnormal CL remodeling in TAFAZZIN deficiency results in defective maturation of skeletal muscle tissue and abnormal mitochondrial function in mature muscle cells.
Methods: To assess the developmental and functional effects of TAFAZZIN deficiency in skeletal muscle cells (SKMs), we used CRISPR-edited human induced pluripotent stem cells to generate TAFAZZIN-knockout (TAZ-KO) and WT skeletal muscle precursors, myoblasts, and myotubes, representing the full range of developing, regenerating, and mature skeletal muscle cells.
Results: We made three novel discoveries using this model. First, we identified abnormal maturation of TAZ-KO SKMs as evidenced by failure to upregulate and sustain myogenic transcription factors including MyoD and MyoG at multiple stages of muscle differentiation. Secondly, we discovered abnormal OXPHOS complex assembly in TAZ-KO muscle precursors by blue native PAGE analysis, where we identified a reduction in assembled CIII-CIV-CV intermediate complexes, with a comparative increase in CIV monomers. Notably, the stabilization of CIII-CIV has been shown to be facilitated by cardiolipin binding, and similar decreases in CIII-CIV-containing complexes have been demonstrated in other TAZ-deficient cell types, including neural precursors. Thirdly, we performed a lipidomic analysis of cardiolipin species and found an increased monolysocardiolipin to cardiolipin ratio in all SKMs, confirming the main clinical biochemical manifestation of BTHS. Interestingly, we also observed unexpected and novel cell-stage genotype and phenotype-specific cardiolipin side chain differences that become more apparent with maturation.
Conclusion: This SKM model of BTHS is the first of its kind and provides a platform with which to investigate the developmental SKM pathology of BTHS, which remains largely unexplored. Overall, our results have implications for understanding the tissue-specific pathology of BTHS and highlights new targets with which to test the effects of potential therapeutics including cardiolipin-modifying small molecules.